
1 Case of Significant Hemorrhage After Nephrostomy Tube Removal
- A 76-year-old male patient who underwent percutaneous nephrostomy for obstructive pyelonephritis experienced sudden and substantial bleeding immediately after his nephrostomy tube was removed on postoperative day 5, according...
- The patient initially presented to clinicians with asymptomatic gross hematuria and a medical history of hypertension, though he was not taking antiplatelet or anticoagulant medications.
- The patient subsequently developed right obstructive pyelonephritis, prompting a right percutaneous nephrostomy using an 8.3-Fr JINRO nephrostomy catheter manufactured by Boston Scientific.
A 76-year-old male patient who underwent percutaneous nephrostomy for obstructive pyelonephritis experienced sudden and substantial bleeding immediately after his nephrostomy tube was removed on postoperative day 5, according to a case report published in Cureus. While hemorrhagic complications during catheter placement are well documented in medical literature, clinically significant bleeding triggered by the removal of the tube itself is rarely reported.
Patient History and Initial Presentation of Bladder Cancer
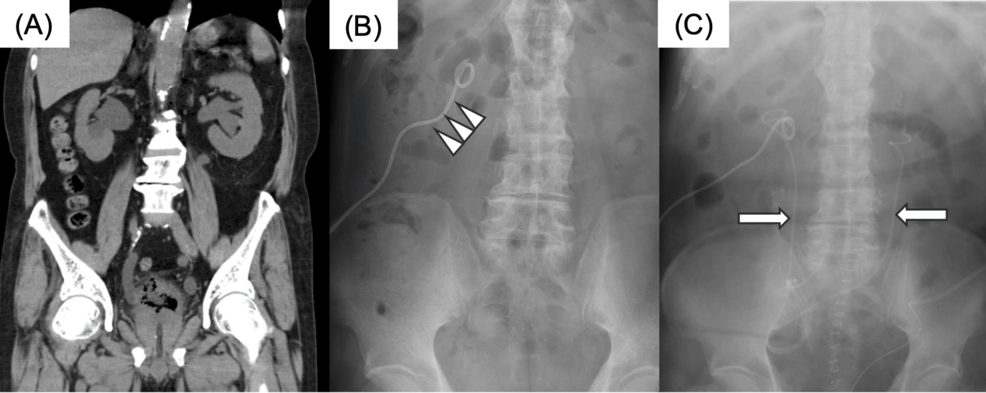
The patient initially presented to clinicians with asymptomatic gross hematuria and a medical history of hypertension, though he was not taking antiplatelet or anticoagulant medications. Magnetic resonance imaging indicated cT3a bladder cancer, while computed tomography revealed cN0M0 disease accompanied by bilateral hydronephrosis. His initial laboratory results showed a serum creatinine level of 1.41 mg/dL and a hemoglobin level of 12.7 g/dL. Following transurethral resection of the bladder tumor, pathological examination confirmed grade 3 urothelial carcinoma according to the 1973 World Health Organization grading system, with muscularis propria invasion matching at least pT2 classification.
Catheter Placement and Subsequent Surgical Intervention
The patient subsequently developed right obstructive pyelonephritis, prompting a right percutaneous nephrostomy using an 8.3-Fr JINRO nephrostomy catheter manufactured by Boston Scientific. The procedure was performed under ultrasound and fluoroscopic guidance without Doppler imaging. A small amount of bleeding was observed through the puncture needle during initial access, but clinicians proceeded with catheter insertion as planned. Five days later, the patient underwent a radical cystectomy, pelvic lymph node dissection, and ileal conduit urinary diversion. The operative time lasted 261 minutes with an estimated blood loss of 610 mL, and the nephrostomy tube was clamped following the procedure and later removed 10 days after its initial placement.
Bleeding Occurs After Nephrostomy Tube Removal
Immediately after the nephrostomy tube was pulled, substantial bleeding erupted from the nephrostomy tract alongside a large volume of bloody output with clots passing through the ileal conduit. Just prior to removal, the patient’s blood pressure registered at 159/75 mmHg with a heart rate of 82 beats per minute. At the onset of the hemorrhage, his blood pressure dropped to 124/65 mmHg and his heart rate climbed to 96 beats per minute. Although the patient remained hemodynamically stable, his hemoglobin level dropped from 10.4 to 9.4 g/dL. Medical staff applied external compression at the nephrostomy site and temporarily inflated a Foley catheter balloon inside the ileal conduit to block the outlet. Contrast-enhanced computed tomography showed no active contrast extravasation but confirmed a hematoma inside the right renal pelvis, alongside approximately 300 g of bloody output and clots retrieved from the conduit. Due to the severity of the bleeding and ongoing blood loss concerns, clinicians administered four units of packed red blood cells, successfully achieving hemostasis without requiring transcatheter arterial embolization.