
Cleveland Clinic develops prehospital extracorporeal CPR program
- Approximately 370,000 cases of out-of-hospital cardiac arrest occur each year in the United States, and fewer than 10% of patients survive to hospital discharge.
- For patients with initial shockable rhythms such as ventricular fibrillation or pulseless ventricular tachycardia, the survival rate is approximately 30%.
- By mechanically restoring systemic circulation and blood oxygenation, the intervention maintains end-organ perfusion.
Approximately 370,000 cases of out-of-hospital cardiac arrest occur each year in the United States, and fewer than 10% of patients survive to hospital discharge. To address this survival gap, Cleveland Clinic developed a prehospital extracorporeal cardiopulmonary resuscitation program to deliver rapid mechanical circulatory support for patients within Cleveland, Ohio.
Refractory Cardiac Arrest Survival Drops Sharply
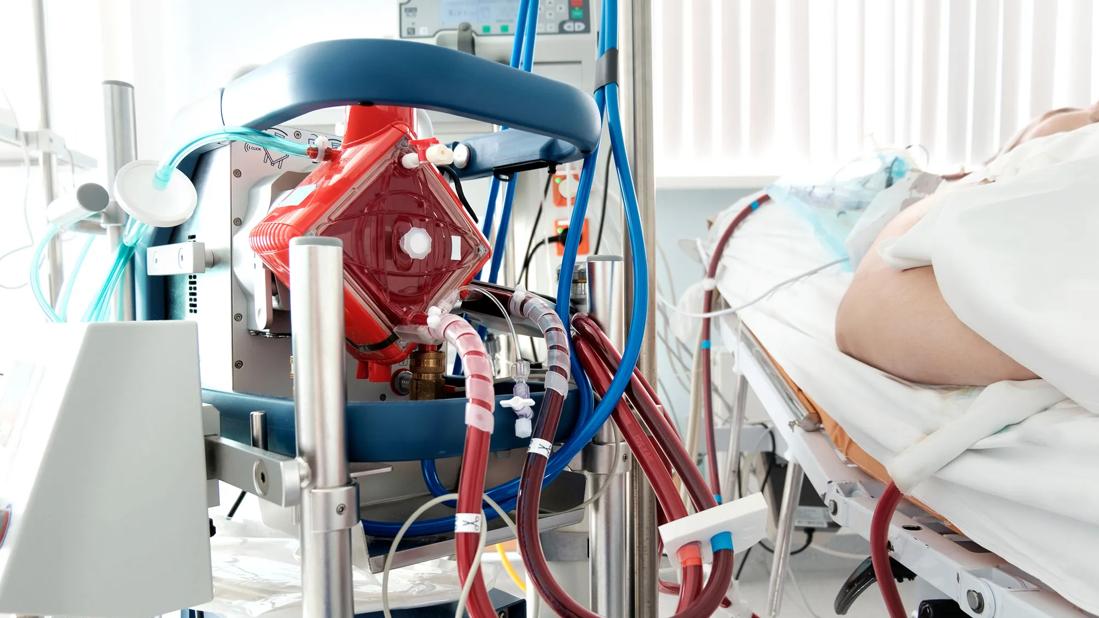
For patients with initial shockable rhythms such as ventricular fibrillation or pulseless ventricular tachycardia, the survival rate is approximately 30%. However, when those rhythms prove refractory to standard resuscitation by requiring more than three shocks or 10 minutes of cardiopulmonary resuscitation, survival falls to roughly 5%. Extracorporeal cardiopulmonary resuscitation serves as a critical bridge in this setting by using rapid initiation of venoarterial extracorporeal membrane oxygenation during active cardiac arrest.
By mechanically restoring systemic circulation and blood oxygenation, the intervention maintains end-organ perfusion. This allows a clinical team to diagnose and reverse the underlying cause of arrest, such as an acute coronary occlusion. While the utility of extracorporeal cardiopulmonary resuscitation is well established for in-hospital cardiac arrest, expanding its use to out-of-hospital cases presents significant logistical hurdles.
Building a Prehospital Shock Team Infrastructure
The prehospital initiative builds on the foundation of Cleveland Clinic’s cardiogenic shock team, which was created in 2018 to formalize multidisciplinary management for patients requiring temporary mechanical circulatory support.
We recognized an opportunity to take it one step further by extending this care to community settings. We saw that the ability to create some structure and process when first responders come upon someone in cardiac arrest could improve survival by enabling institution of ECMO in less than an hour after OHCA — and ideally considerably sooner.
Edward Soltesz, MD, MPH
Dr. Soltesz notes that the steps leading up to cannulation represent an operations nightmare involving communication streams between field providers and hospital teams, coordination between cardiovascular and emergency department staff, and the rapid deployment of caregivers.
Establishing Protocols and 24/7 Cath Lab Availability
Interventional cardiologist Jacqueline Tamis-Holland led efforts to unravel these complexities by drawing on published literature and the experiences of early adopters in Paris, Minnesota, and Prague. A key takeaway from those programs is that an institution must establish foundational infrastructure before attempting prehospital activation.
Success depends on starting extracorporeal cardiopulmonary resuscitation within 10 to 15 minutes of a patient’s arrival, according to Dr. Tamis-Holland. That requirement demands a cath lab available 24 hours a day, 7 days a week, an ECMO-capable operator on site at all times, fluoroscopy or transesophageal echo to confirm placement, and deep expertise in postprocedural critical care.
To streamline rapid activation, Cleveland Clinic modified its centralized ECMO paging process. Paging operator scripts were refined to eliminate lengthy verbal intake checks so field notifications immediately page out the designated multidisciplinary team. The program also established a cannulator of the day role rotated among primary specialists.
Clear Criteria Ensure Intervention for Patients with Recovery Potential
Establishing clear eligibility criteria ensures the intervention is deployed for patients with a meaningful chance of favorable recovery. Core criteria require patients to be between 18 and 70 years old, have a witnessed arrest, present with an initial rhythm of ventricular fibrillation or pulseless ventricular tachycardia, receive mechanical cardiopulmonary resuscitation, and have an estimated transport time under 30 minutes.
Continuous quality assessment since the program launched in January 2026 has already driven process changes, most notably regarding the site of cannulation. Arriving patients initially underwent point-of-care testing in the emergency department before transport to the cath lab, but that movement added up to 10 minutes of critical low-flow time.
Cleveland Clinic is now transitioning primary cannulation directly into the emergency department, starting with the acquisition of a dedicated fluoroscopy table for the emergency department resuscitation suite. Cath lab nurses, perfusionists, and the designated cannulator now report directly to the emergency department.
Collaborating with Local EMS Providers for Citywide Care
The Cleveland ECPR Program was established in collaboration with local emergency medical services providers and another local academic health center, supported by a Mandel Foundation grant. Prehospital protocols and patient eligibility criteria were developed alongside emergency medical services medical directors to standardize timely care for refractory out-of-hospital cardiac arrest across the city.
The program maintains active engagement with local emergency services and the Cleveland community by providing regular feedback to paramedic squads and hosting educational events. Plans call for eventual expansion beyond the Main Campus and the initial partner hospital to other Cleveland Clinic facilities located within or near Cleveland city limits.