
Delayed Diagnosis of Duchenne Muscular Dystrophy in an 11-Year-Old Boy Presenting with Acute Respiratory Illness: A Case Report
- An 11-year-old boy evaluated for an acute hypoxemic respiratory illness was found to have an undiagnosed case of Duchenne muscular dystrophy, Cureus reported.
- Parents reported that the boy's lower-extremity weakness had progressed over several months, making it difficult for him to rise from a seated position.
- Laboratory evaluations ordered during the hospital admission showed a white-cell count of 28.4 × 10⁹/L and a C-reactive protein level of 66, indicating a concurrent lower respiratory tract...
An 11-year-old boy evaluated for an acute hypoxemic respiratory illness was found to have an undiagnosed case of Duchenne muscular dystrophy, Cureus reported. The patient presented with a fever, productive cough, and a blood oxygen saturation level between 88% and 90% on room air. Medical staff treated his acute infection while uncovering a severe, long-standing neuromuscular condition that had gone unrecognized despite early developmental delays.
Delayed Motor Findings Emerge During Respiratory Treatment
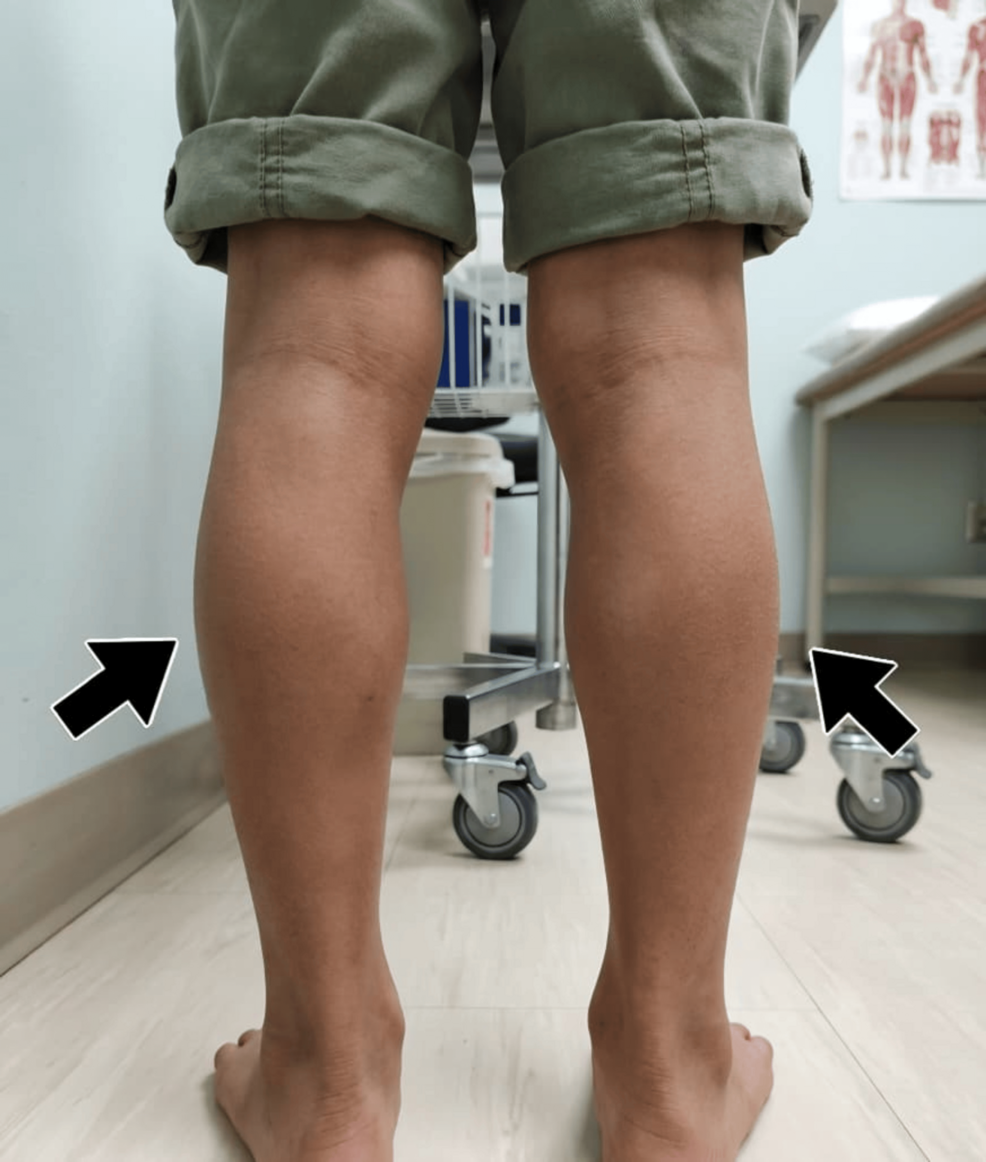
Parents reported that the boy’s lower-extremity weakness had progressed over several months, making it difficult for him to rise from a seated position. A history of delayed motor milestones in early childhood was revealed, though he had never undergone a formal neuromuscular evaluation. A physical examination revealed bilateral calf pseudohypertrophy, hypotonia, and diminished deep tendon reflexes in the lower extremities. When attempting to stand, the patient used his hands to push off his legs, demonstrating a Gowers maneuver that pointed toward significant proximal muscle weakness.
Extremity Weakness Meets Acute Lung Infection
Laboratory evaluations ordered during the hospital admission showed a white-cell count of 28.4 × 10⁹/L and a C-reactive protein level of 66, indicating a concurrent lower respiratory tract infection. Simultaneously, the patient’s serum creatine kinase concentration reached 8,500 U/L, which is approximately 34 times the upper reference limit. Aspartate aminotransferase and alanine aminotransferase levels were also mildly elevated at 50 U/L and 55 U/L, respectively. Clinicians noted that this enzyme elevation stemmed from skeletal muscle injury rather than hepatobiliary disease.
Genetic Testing Confirms Dystrophinopathy Without Biopsy
Multiplex ligation-dependent probe amplification and confirmatory next-generation sequencing identified a hemizygous deletion of exons 45 through 50 of the DMD gene located at Xp21.2. This genetic finding established a definitive diagnosis of Duchenne muscular dystrophy without requiring an invasive muscle biopsy. Medical teams managed the respiratory illness separately using supplemental oxygen, empiric intravenous broad-spectrum antibiotics, and chest physical therapy.
Multidisciplinary Management and Mutation-Specific Care
Following respiratory stabilization, the patient received referrals for multidisciplinary neuromuscular management and genetic counseling. Proposed long-term interventions include corticosteroid therapy, regular physical therapy and stretching, nutritional support, and ongoing cardiac and respiratory surveillance through electrocardiography, echocardiography, and pulmonary function testing. Because the identified deletion of exons 45 to 50 can potentially be addressed with exon 51-skipping therapy, clinicians recommended an assessment for mutation-specific treatment depending on regulatory criteria and clinical availability.
Data from population-based surveillance studies cited in the report indicate a typical diagnostic interval where first documented signs appear at a mean age of 2.7 years while confirmation occurs at 4.9 years. Diagnosis at 11 years highlights a substantial delay in recognition, though the absence of early developmental records leaves the exact onset of symptoms unmeasured and the specific missed opportunities for earlier intervention undetermined.