
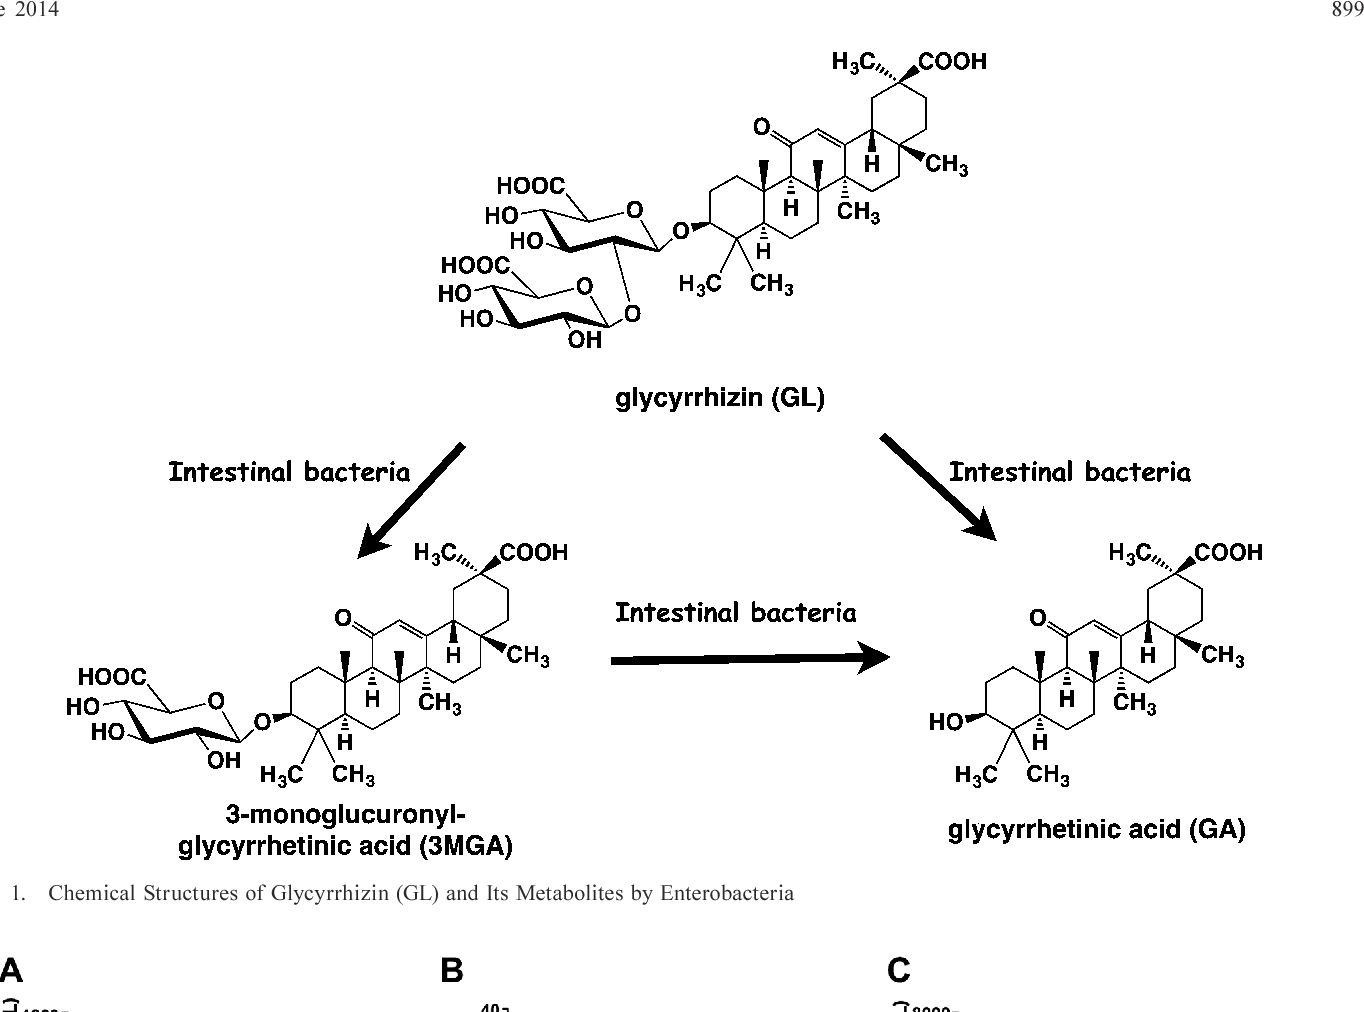
Glycyrrhizin-Induced Pseudoaldosteronism and Decompensated HFpEF
Glycyrrhizin-induced pseudoaldosteronism has been identified as a critical contributing factor in cases of decompensated heart failure with preserved ejection fraction, according to medical findings published in the journal Cureus. This condition occurs when exposure to glycyrrhizin—a primary active compound found in licorice root and certain traditional herbal remedies—triggers severe electrolyte imbalances that mimic excess aldosterone production.
Understanding Glycyrrhizin-Induced Pseudoaldosteronism
The physiological mechanism involves the inhibition of the enzyme 11-beta-hydroxysteroid dehydrogenase type 2 in the kidneys. According to the Cureus report, this enzymatic block prevents the conversion of cortisol to cortisone, leading to an excess of cortisol activating mineralocorticoid receptors. Consequently, patients experience profound sodium retention, potassium loss, and hypertension, which can severely strain the cardiovascular system.
In patients with underlying vulnerabilities, such as older adults or those with pre-existing cardiac conditions, this biochemical disruption can precipitate acute fluid overload. The resulting hemodynamic burden frequently manifests as decompensated heart failure with preserved ejection fraction, a complex clinical scenario where the heart muscle remains able to contract well during relaxation phases but struggles to handle increased volume and pressure.
Clinical Implications and Management
Identifying the root cause of pseudoaldosteronism requires a thorough dietary and pharmacological history, specifically screening for regular consumption of licorice-containing products, herbal teas, or specific traditional medicines. Clinicians addressing these presentations typically focus on immediate discontinuation of the offending substance alongside targeted management of electrolyte disturbances and fluid overload.
The documentation in Cureus underscores the necessity for heightened clinical awareness regarding over-the-counter and herbal supplements in vulnerable patient populations. As dietary and herbal exposures are not always volunteered during routine medical intake, targeted questioning remains vital for preventing recurrent cardiovascular complications linked to pseudoaldosteronism.