
Household Transmission of Haemophilus Influenzae Pneumonia in an Elderly Cohabiting Couple
- Two elderly cohabiting adults developed Haemophilus influenzae pneumonia ten days apart at a hospital in Japan, presenting matching minimum inhibitory concentration profiles across all tested antimicrobial agents, Cureus...
- The first patient, a 95-year-old Japanese man with a history of hypertension, dyslipidemia, and hyperuricemia, developed a productive cough and hoarseness three days before his hospital admission.
- Ten days after her husband's admission, his 90-year-old wife presented to the same hospital with worsening dyspnea, general fatigue, and difficulty walking after an outpatient course of amoxicillin/clavulanic...
Two elderly cohabiting adults developed Haemophilus influenzae pneumonia ten days apart at a hospital in Japan, presenting matching minimum inhibitory concentration profiles across all tested antimicrobial agents, Cureus reported. The cases highlight potential household transmission pathways for respiratory pathogens among older adults with underlying health conditions, according to the clinical report published by Cureus and indexed on Semantic Scholar.
Couples hospitalized ten days apart with identical susceptibility isolates
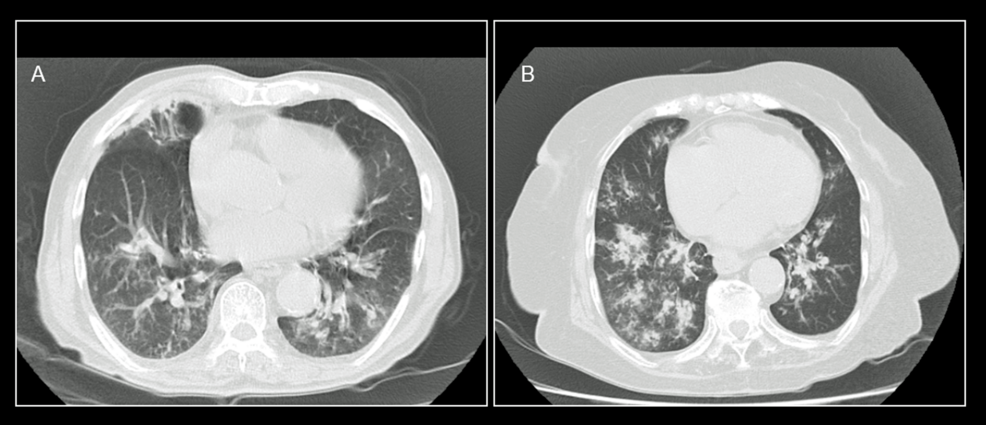
The first patient, a 95-year-old Japanese man with a history of hypertension, dyslipidemia, and hyperuricemia, developed a productive cough and hoarseness three days before his hospital admission. Upon arrival, his body temperature reached 38.7 degrees Celsius, and his oxygen saturation dropped to 85 percent on room air, necessitating three liters per minute of supplemental oxygen. Chest computed tomography revealed infiltrative opacities in his bilateral lower lobes accompanied by a small pleural effusion. Sputum cultures isolated Haemophilus influenzae, and physicians initiated intravenous ampicillin/sulbactam at 12 grams daily. He recovered and was discharged ambulatory on hospital day 14, Cureus reported.
Ten days after her husband’s admission, his 90-year-old wife presented to the same hospital with worsening dyspnea, general fatigue, and difficulty walking after an outpatient course of amoxicillin/clavulanic acid failed to resolve her symptoms. Physicians treated her with intravenous ceftriaxone at two grams daily for 12 days, and she was discharged on hospital day 18 after regaining the ability to walk with a cane, Cureus stated.
Household exposure timeline and wider respiratory symptoms
Prior to the couple’s hospitalizations, other members of the same household experienced respiratory illness, according to the clinical timeline documented in Cureus. The couple lived with their 57-year-old son and his 51-year-old wife. The son developed a sore throat and productive cough 14 days before the male patient’s admission, while the daughter-in-law developed matching symptoms three days prior to that same admission and subsequently improved following outpatient clarithromycin treatment. Neither family member underwent microbiological testing, leaving the causative pathogen for their initial illnesses undetermined.
Wider scientific literature highlights that invasive Haemophilus influenzae disease, including pneumonia and bacteremia, disproportionately affects older adults and younger children, with mortality rates elevated among patients with comorbidities and polymicrobial infections, as noted in studies tracked by Semantic Scholar. Furthermore, nationwide surveillance in Japan has tracked an increasing prevalence of beta-lactamase-non-producing ampicillin-resistant strains carrying alterations in penicillin-binding protein 3, underscoring the clinical importance of monitoring antimicrobial susceptibility profiles in respiratory isolates, Cureus reported.
Unresolved transmission vectors among cohabiting family members
While the recovery of Haemophilus influenzae isolates with identical minimum inhibitory concentration profiles from both spouses provides circumstantial evidence consistent with household transmission, molecular epidemiological analyses and serotyping were not performed to definitively confirm strain identity, Cureus noted. Consequently, investigators could not exclude infection originating from a distinct external source, nor could they establish the precise direction of transmission within the household given the unverified pathogen status of the son and daughter-in-law.
