
ILCOR Recommends Higher Initial FiO2 for Preterm Infant Resuscitation
- Oxygen therapy titration for extremely preterm infants requires balancing the competing risks of hypoxia and hyperoxia during neonatal stabilization, analesdepediatria.org reported.
- Systematic reviews comparing low initial fractions of inspired oxygen at 0.5 or below against high initial fractions above 0.5 find no significant differences in mortality or major neonatal...
- For decades, clinicians used high oxygen concentrations to rapidly reverse hypoxia in newborns.
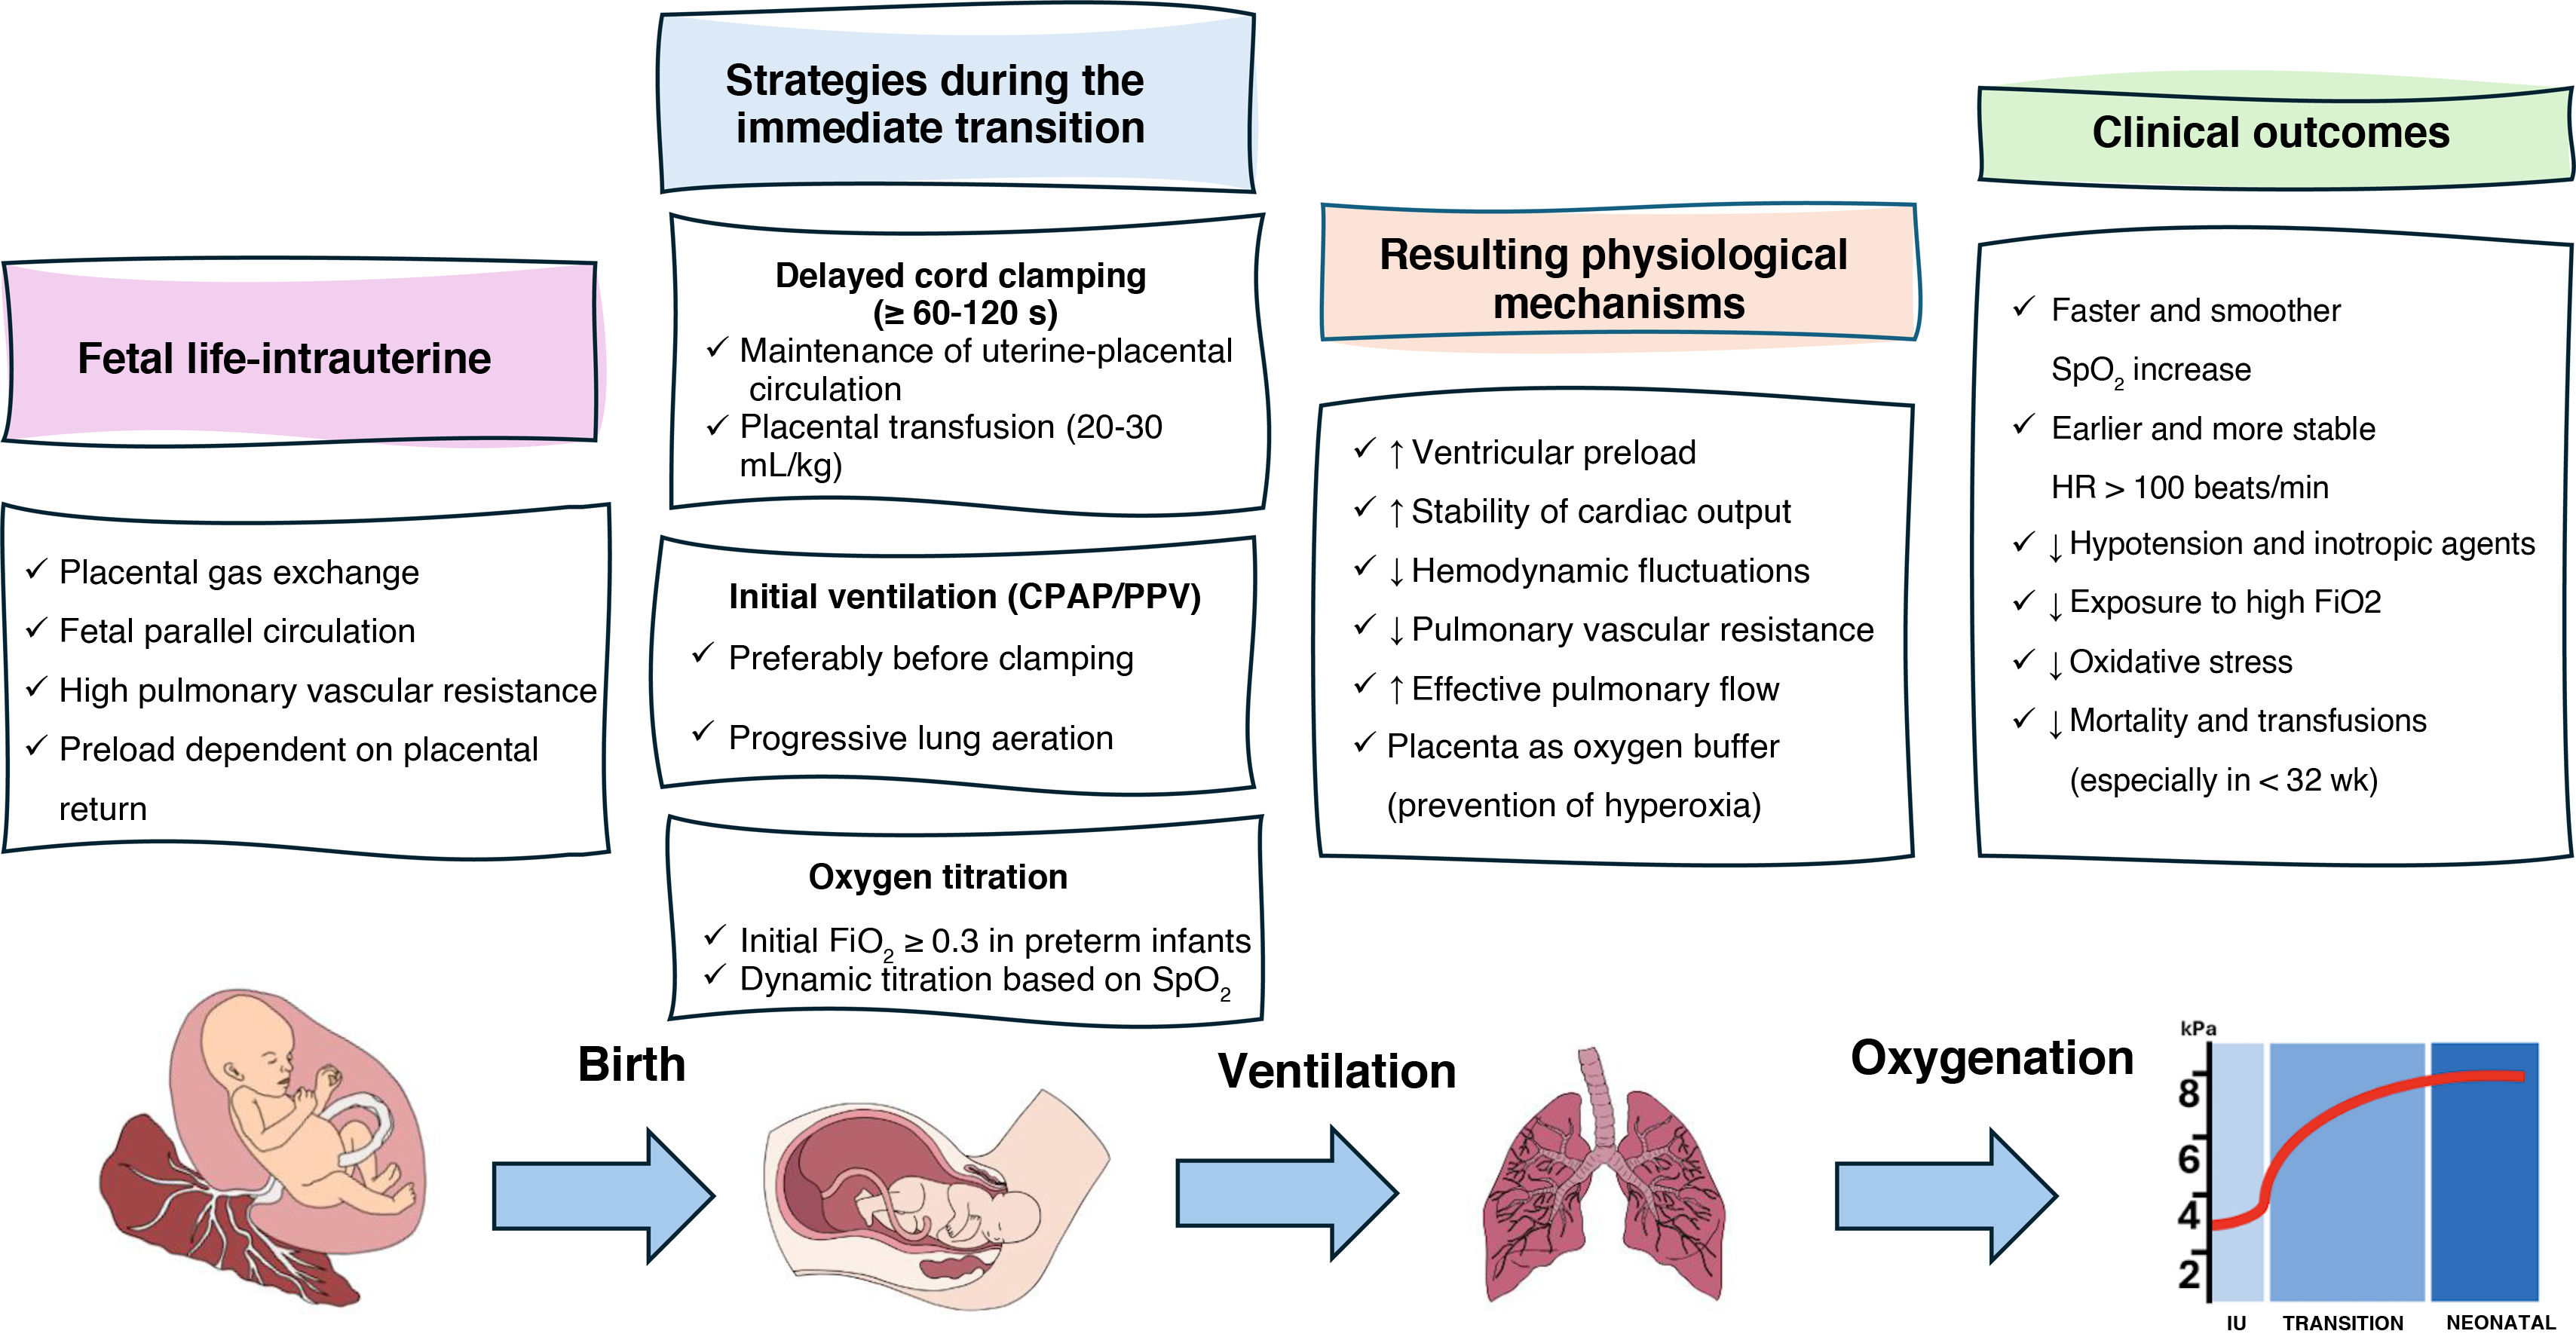
Oxygen therapy titration for extremely preterm infants requires balancing the competing risks of hypoxia and hyperoxia during neonatal stabilization, analesdepediatria.org reported. Hypoxemia in the first minutes of life correlates with prolonged bradycardia, hemodynamic instability, severe intraventricular hemorrhage, and increased mortality. Conversely, hyperoxia promotes oxidative stress and raises the risk of lung, brain, and retinal injury.
Initial Oxygen Strategies and Mortality Risks
Systematic reviews comparing low initial fractions of inspired oxygen at 0.5 or below against high initial fractions above 0.5 find no significant differences in mortality or major neonatal complications. However, the overall quality of available evidence remains low due to study heterogeneity. A post hoc analysis of the TORPIDO trial demonstrated increased mortality and poorer neurodevelopmental outcomes in extremely preterm infants born before 28 weeks of gestation who were initially stabilized with room air when their oxygen saturation failed to reach at least 80% at five minutes post birth.
For decades, clinicians used high oxygen concentrations to rapidly reverse hypoxia in newborns. Subsequent findings regarding oxidative stress led to recommendations favoring an initial fraction of inspired oxygen between 0.21 and 0.30 for preterm stabilization. Many of those foundational studies involved newborns subjected to immediate cord clamping, which limits the extrapolation of findings to modern physiological-based transition strategies. Subsequent data showed that many very premature infants fail to reach target saturations when stabilization starts at an oxygen fraction of 0.30. Consequently, the International Liaison Committee on Resuscitation recommends starting respiratory stabilization in preterm infants born before 32 weeks with a fraction of inspired oxygen greater than 0.30, followed by titration based on continuous monitoring.