
Multisystemic Sarcoidosis Causes Acute Kidney Injury and Seizures
- A patient presented to an emergency department with severe acute kidney injury, seizures, and hematological involvement, leading to a diagnosis of multisystemic sarcoidosis.
- The patient, who had no prior significant medical history, arrived at the emergency department following generalized tonic-clonic seizures that required midazolam for termination and subsequent mechanical ventilation due...
- Systematic investigation in the intensive care unit uncovered a broad range of systemic issues.
A patient presented to an emergency department with severe acute kidney injury, seizures, and hematological involvement, leading to a diagnosis of multisystemic sarcoidosis. The case, documented by researchers in the journal Cureus, highlights the diagnostic challenges clinicians face when sarcoidosis presents with severe nonpulmonary symptoms that mimic other metabolic or systemic conditions.
Clinical Presentation and Emergency Admission
The patient, who had no prior significant medical history, arrived at the emergency department following generalized tonic-clonic seizures that required midazolam for termination and subsequent mechanical ventilation due to airway compromise. Upon admission, initial laboratory testing revealed severe metabolic acidemia with a pH of 6.8 and bicarbonate levels at 4 mmol/L. His renal function was critically impaired, with creatinine reaching 13.65 mg/dL, classified as KDIGO stage 3 acute kidney injury.
Diagnostic Investigations and Multisystem Findings
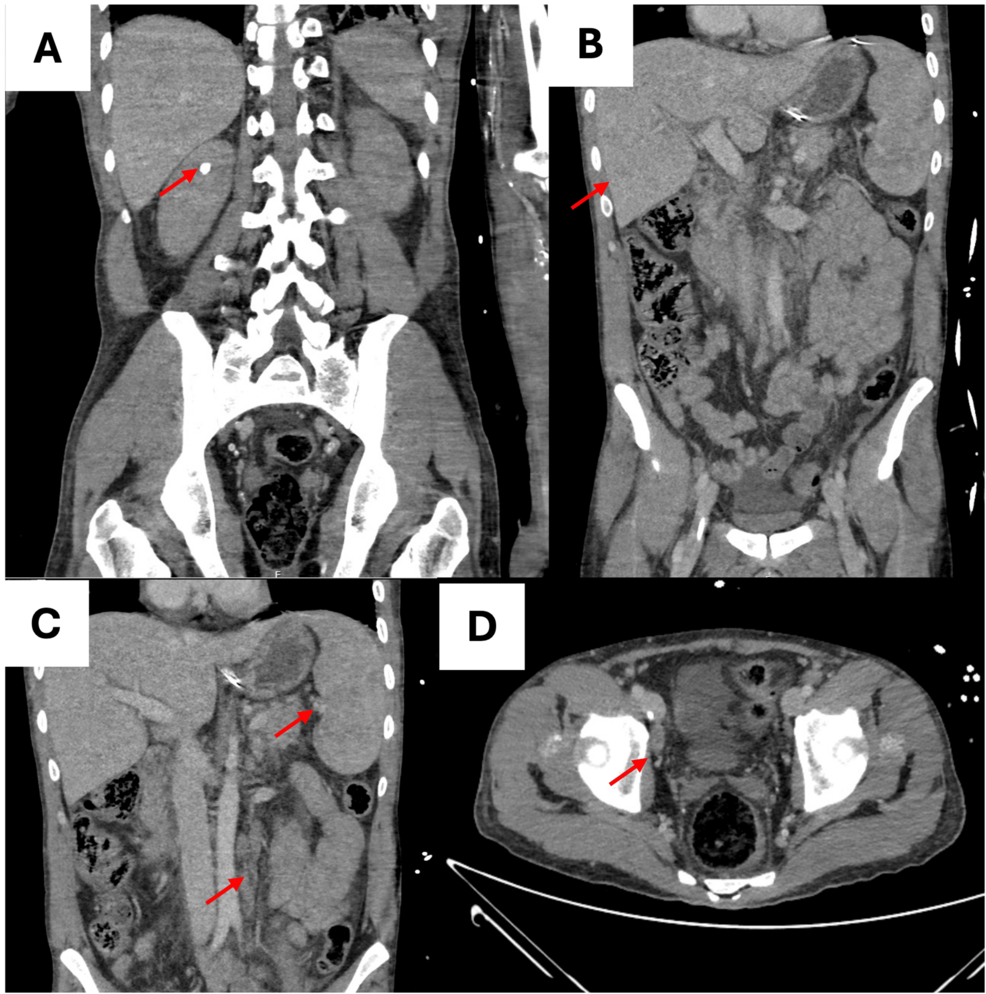
Systematic investigation in the intensive care unit uncovered a broad range of systemic issues. Hematological workup identified pancytopenia, characterized by leukopenia, anemia, and thrombocytopenia, alongside undetectable haptoglobin and elevated lactate dehydrogenase. Thoracoabdominal computed tomography scans showed hepatomegaly, splenomegaly, and extensive lymphadenopathy in the retroperitoneal, iliac, and inguinal regions. Imaging also revealed reduced cortical contrast enhancement of the kidneys with perinephric fat stranding.
Further laboratory analysis showed significantly elevated serum angiotensin-converting enzyme at 197.4 U/L. Lymphocyte immunophenotyping revealed marked T-cell lymphopenia with an inverted CD4/CD8 ratio. While initial neurological concerns were high, brain magnetic resonance imaging showed only nonspecific white matter changes and a small hypointense focus, helping to rule out primary central nervous system infection.
Granulomatous Interstitial Nephritis Identification
Due to the severity of the renal failure, physicians performed a renal biopsy. The procedure identified a polymorphic inflammatory infiltrate containing non-necrotizing granulomas. This finding, described as granulomatous interstitial nephritis, confirmed the diagnosis of sarcoidosis. The patient also presented with new-onset hypothyroidism, which required the initiation of levothyroxine therapy during his intensive care stay.
Management of Complicated Sarcoidosis
The patient’s management required sustained low-efficiency daily dialysis to address uremic syndrome and significant nitrogenous waste retention. The medical team noted that the case illustrates the difficulty of attributing symptoms to sarcoidosis when metabolic and disease-specific causes appear to coexist. The researchers emphasized that while pulmonary involvement is standard for sarcoidosis diagnosis, nonpulmonary presentations often lead to management challenges and diagnostic delays. The patient’s recovery of renal function was achieved through the intensive care interventions and ongoing systemic therapy.