
SMC Approves Vutrisiran for ATTR-CM Treatment in NHS Scotland
- The Scottish Medicines Consortium (SMC) has approved vutrisiran sodium (Amvuttra) for restricted use within NHS Scotland to treat adults with transthyretin amyloidosis with cardiomyopathy (ATTR-CM).
- Access to the treatment is contingent upon an approved patient access scheme (PAS) that ensures cost-effectiveness.
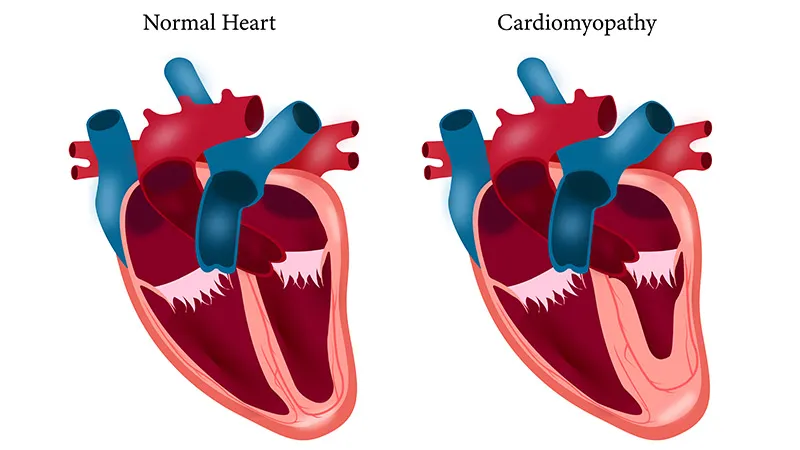
- ATTR-CM is a progressive disease characterized by the buildup of transthyretin (TTR) amyloid deposits in the heart, which causes the organ to stiffen and eventually fail.
The Scottish Medicines Consortium (SMC) has approved vutrisiran sodium (Amvuttra) for restricted use within NHS Scotland to treat adults with transthyretin amyloidosis with cardiomyopathy (ATTR-CM). The decision, as reported by Medscape, authorizes the drug as a monotherapy for patients with both wild-type and hereditary forms of the rare, fatal condition.
Access to the treatment is contingent upon an approved patient access scheme (PAS) that ensures cost-effectiveness. The SMC’s guidance stipulates that the medication must be provided at a PAS or list price equivalent to or lower than the agreed-upon threshold.
Understanding the Mechanism of Vutrisiran
ATTR-CM is a progressive disease characterized by the buildup of transthyretin (TTR) amyloid deposits in the heart, which causes the organ to stiffen and eventually fail. These deposits can also accumulate in the gastrointestinal tract and peripheral nerves. While wild-type ATTR-CM typically develops due to structural instability of TTR protein as patients age, hereditary ATTR-CM is linked to more than 120 specific genetic mutations.
Vutrisiran functions as a small interfering RNA (siRNA) therapy. By utilizing RNA interference, the drug suppresses the liver’s production of both variant and wild-type TTR protein. Reducing these circulating levels of TTR protein limits the formation of amyloid deposits in tissues.
Evidence from the HELIOS-B Clinical Trial
The SMC’s decision is based on findings from the phase 3 HELIOS-B trial, which enrolled 655 patients with ATTR-CM and a history of heart failure. Participants received either 25 mg of vutrisiran or a placebo via subcutaneous injection every 12 weeks for a duration of up to 36 months.
Data showed that vutrisiran significantly lowered the risk of a composite outcome—all-cause mortality and recurrent cardiovascular events—compared to the placebo. In the monotherapy subgroup, which represents the population covered by the new SMC restriction, the hazard ratio (HR) was 0.67 (95% CI, 0.49-0.93). All-cause mortality at 42 months for this subgroup was 22% for those on vutrisiran versus 29% for those receiving the placebo.
Beyond survival metrics, the treatment demonstrated functional benefits. At 30 months, patients treated with vutrisiran experienced a slower decline in 6-minute walk distance and higher health status scores on the Kansas City Cardiomyopathy Questionnaire compared to the placebo group.
Safety Profile and Prescribing Considerations
The safety profile of vutrisiran was found to be consistent with existing data, with no new safety concerns identified during the trial. Adverse events occurred at similar rates between the treatment and placebo groups, with serious adverse events reported in 62% of patients receiving vutrisiran and 67% of those receiving the placebo. The most frequent serious adverse events included cardiac failure and atrial fibrillation.
The recommended dosage is 25 mg delivered via subcutaneous injection every three months. Because the therapy can lower vitamin A levels, patients are required to take daily vitamin A supplements, typically providing 2,500 to 3,000 IU. The SMC advises that clinicians should initiate treatment as early as possible to mitigate disability accumulation.
Vutrisiran offers another treatment option for patients with ATTR-CM, that is administered in a different way from the currently available option and may suit some patients better.
Dr. Rob Peel, SMC Chair
Clinical Uncertainties and Limitations
Despite the approval, the SMC highlighted several areas of uncertainty. Data regarding indirect comparisons between vutrisiran and tafamidis—the only other therapy currently accepted for ATTR-CM in Scotland—remain limited. A post hoc comparison suggested no significant difference in outcomes between the two drugs, but the SMC noted this analysis was not pre-specified and may have been influenced by bias, as patients already on tafamidis likely experienced clinical benefits at baseline.
Additionally, the SMC noted that hereditary ATTR-CM represented only 12% of the HELIOS-B trial population. While subgroup analysis indicated a potential benefit in these patients, the small sample size requires cautious interpretation. Despite these uncertainties, clinical experts consulted by the SMC classified vutrisiran as a therapeutic advancement due to its novel mechanism of action, positioning it as an effective alternative to existing management strategies.