
Switching From Clopidogrel to Ticlopidine and Ginkgo Leaf Extract Due to Side Effects in Coil Embolization
- Medical practitioners reported a case where a patient who underwent coil embolization switched from Clopidogrel to a combination of Ticlopidine and Ginkgo leaf extract after experiencing adverse reactions.
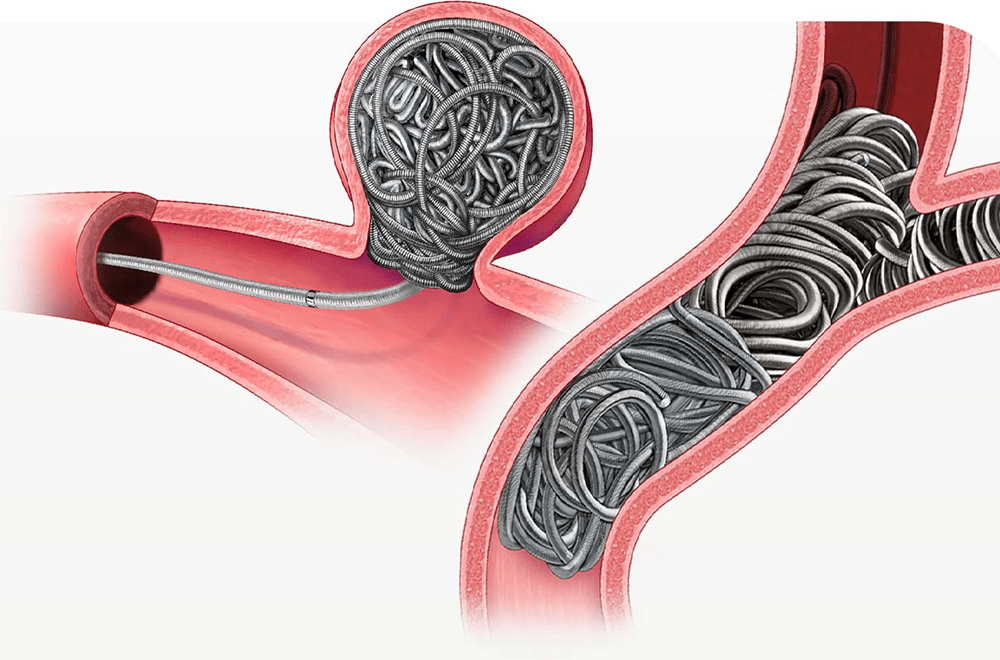
- The patient had received coil embolization, a procedure used to treat brain aneurysms by filling the aneurysm with platinum coils to block blood flow and prevent rupture.
- Clinical teams transitioned the patient to Ticlopidine, another P2Y12 inhibitor, supplemented with Ginkgo leaf extract.
Medical practitioners reported a case where a patient who underwent coil embolization switched from Clopidogrel to a combination of Ticlopidine and Ginkgo leaf extract after experiencing adverse reactions. According to the Medical Observer, this alternative regimen was used to maintain necessary antiplatelet therapy and prevent clot formation following the procedure.
The patient had received coil embolization, a procedure used to treat brain aneurysms by filling the aneurysm with platinum coils to block blood flow and prevent rupture. To prevent the blood from clotting on these coils, doctors typically prescribe antiplatelet medications. The Medical Observer reported that the patient was initially treated with Clopidogrel, a common P2Y12 inhibitor, but developed side effects that necessitated a change in medication.
Clinical teams transitioned the patient to Ticlopidine, another P2Y12 inhibitor, supplemented with Ginkgo leaf extract. This combination served as a substitute to ensure the patient remained protected against thromboembolic events while avoiding the specific reactions triggered by Clopidogrel.
Why is antiplatelet therapy required after coil embolization?
Antiplatelet therapy prevents the formation of blood clots that can occur when foreign materials, such as platinum coils, are introduced into a blood vessel. If a clot forms on the coil, it can lead to an ischemic stroke by blocking blood flow to parts of the brain, according to medical standards for neurovascular intervention.

Clopidogrel is often the first choice for this therapy because it generally has a more favorable safety profile than older medications. However, some patients experience adverse reactions or are “non-responders” due to genetic variations in the CYP2C19 enzyme, which the body uses to activate the drug.
When Clopidogrel is not tolerated, physicians must find an alternative that provides similar inhibition of platelet aggregation. In this specific case reported on June 14, 2026, the medical team opted for Ticlopidine, which is an earlier generation antiplatelet agent.
How does Ginkgo leaf extract support this treatment?
Ginkgo biloba leaf extract acts as an adjuvant to antiplatelet therapy by inhibiting Platelet Activating Factor (PAF). According to pharmacological research, PAF is a potent phospholipid that triggers platelet aggregation and vasoconstriction.

By combining Ticlopidine with Ginkgo leaf extract, the treatment targets two different pathways of platelet activation. Ticlopidine blocks the ADP receptor on the platelet surface, while the Ginkgo extract reduces the influence of PAF. This dual approach helps maintain blood fluidity and reduces the risk of thrombus formation on the embolization coils.
The use of Ginkgo extract in this context is intended to bolster the anti-clotting effect, potentially allowing for effective management even when standard primary therapies like Clopidogrel are unavailable due to patient intolerance.
What are the risks associated with Ticlopidine?
While effective, Ticlopidine carries a higher risk of severe side effects compared to Clopidogrel. The most critical concern is neutropenia, a condition where the white blood cell count drops to dangerously low levels, increasing the risk of infection.

Because of this risk, patients on Ticlopidine typically require regular blood monitoring. Medical guidelines suggest frequent complete blood counts (CBC) during the first few months of treatment to detect early signs of bone marrow suppression.
The decision to switch to Ticlopidine and Ginkgo leaf extract represents a calculated trade-off. The medical team prioritized the immediate need for antiplatelet protection over the potential risks of Ticlopidine, provided the patient is closely monitored.
This case highlights the necessity of personalized medicine in neurovascular care. When standard protocols fail due to patient-specific adverse reactions, clinicians may rely on a combination of older pharmaceutical agents and botanical extracts to achieve the required therapeutic outcome.