
ESO-T01 BCMA CAR-T Clinical Trial Terminated Following Corporate Acquisition
- A clinical trial evaluating a CAR-T therapy for relapsed or multiple myeloma has been terminated following a corporate acquisition.
- ESO-T01 was developed to encode an anti-BCMA chimeric antigen receptor using a self-inactivating vector system.
- The study was halted because original sponsor EsoBiotec was acquired by AstraZeneca.
A clinical trial evaluating a CAR-T therapy for relapsed or multiple myeloma has been terminated following a corporate acquisition. The phase 1 study at Wuhan Union Hospital was testing ESO-T01, a third-generation lentiviral vector designed to target B-cell maturation antigen.
ESO-T01 was developed to encode an anti-BCMA chimeric antigen receptor using a self-inactivating vector system. Investigators aimed to evaluate safety, tolerability, and preliminary efficacy in patients who had experienced disease progression after at least two prior lines of therapy.
Corporate Acquisition Triggers Trial Termination at Wuhan Union Hospital
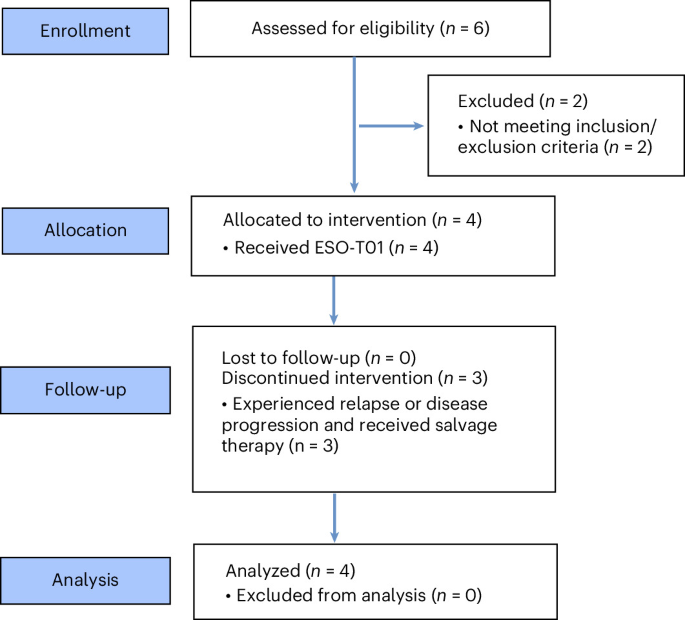
The study was halted because original sponsor EsoBiotec was acquired by AstraZeneca. No additional patient enrollments are permitted under the updated trial terms registered on ClinicalTrials.gov on November 9, 2024, leaving the cohort capped at its pre-termination size.
Prior to the shutdown, the clinical protocol underwent a formal amendment. The changes permitted prophylactic glucocorticoid use before infusions, widened inclusion criteria to capture clinical relapse events, and updated 24-hour urine collection requirements for protein electrophoresis assessments.
Trial Participants Must Have BCMA Positive Multiple Myeloma
Participants in the single-arm open-label trial required confirmed multiple myeloma diagnoses with positive BCMA expression verified by flow cytometry or bone marrow pathology. Patients also needed to demonstrate refractoriness to both immunomodulators and proteasome inhibitors alongside measurable disease parameters.
The experimental construct incorporates an anti-BCMA nanobody, a CD8 alpha hinge and transmembrane domain, a 4-1BB co-stimulatory domain, and a CD3 zeta signaling domain. To boost T-cell selectivity and limit off-target transduction, the vector utilizes a mutant vesicular stomatitis virus glycoprotein envelope, CD47 overexpression, major histocompatibility complex class I knockout, and an anti-TCR nanobody.
Safety Endpoints and Biomarker Monitoring
Primary endpoints for the trial focused on documenting safety and tolerability, including dose-limiting toxicities and adverse events. Secondary endpoints tracked objective response rates, measurable residual disease negativity, pharmacokinetics, and pharmacodynamic profiles including interleukin-6 and ferritin levels.
Researchers utilized flow cytometry to monitor vector copy numbers and evaluate peripheral T-cell phenotypes.
Participants Must Be Adults with Specific Performance Scores
All participants provided written informed consent before any study-related procedures. Treatment and related procedures were provided free of charge, with reimbursement for transportation and nutrition supplied for each blood collection and follow-up visit. Sex was assessed via participant self-report, and disaggregated analysis by sex was not performed due to the small size of the cohort.
Major inclusion criteria required participants to be at least 18 years of age, have an Eastern Cooperative Oncology Group performance status score of 0 to 2, and an expected survival of at least 3 months. Relapse or disease progression was required within 12 months before screening, alongside progressive disease during or within 2 months after the most recent antimyeloma therapy.
Additional screening requirements within 2 months prior included bone marrow function tests showing hemoglobin at least 6 g dl−1, absolute neutrophil count at least 600 microliters−1, platelet count at least 50,000 microliters−1, lymphocyte count at least 500 microliters−1, and absolute CD3+ T cell count at least 150 microliters−1. Renal function required creatinine clearance of at least 45 ml min−1 using the Cockcroft-Gault formula. Liver function parameters mandated ALT and AST up to 3.0 times the upper limit of normal, total bilirubin and alkaline phosphatase up to 2.0 times the upper limit of normal, and albumin at least 3 g dl−1. Cardiac function required a left ventricular ejection fraction of at least 40% with no clinically important pericardial effusion or electrocardiogram abnormalities, and pulmonary function parameters were also evaluated.
Cells were incubated with biotinylated human BCMA protein for 40 minutes, washed with phosphate-buffered saline, and stained with CD3 APC and PE-streptavidin for 15 minutes. The Bio-Rad CFX96 System was used for quantification, and immunohistochemistry staining for CD38, CD138, CS1, and BCMA was performed on formalin-fixed paraffin-embedded sections using a Titan automated stainer.