
Medical review details cardiac biomarkers in myocardial infarction
- Cardiovascular diseases account for approximately one-third of all annual deaths globally, with acute myocardial infarction standing as a primary contributor to worldwide mortality and healthcare expenditure.
- Acute myocardial infarction involves acute myocardial injury accompanied by evidence of myocardial ischemia.
- Biochemical biomarkers provide objective evidence of myocardial damage in clinical practice.
Cardiovascular diseases account for approximately one-third of all annual deaths globally, with acute myocardial infarction standing as a primary contributor to worldwide mortality and healthcare expenditure. The medical review details the biochemical characteristics, physiological basis, and diagnostic limits of ischemia-modified albumin alongside conventional cardiac biomarkers.
Acute Myocardial Infarction Mechanics and Biomarker Evolution
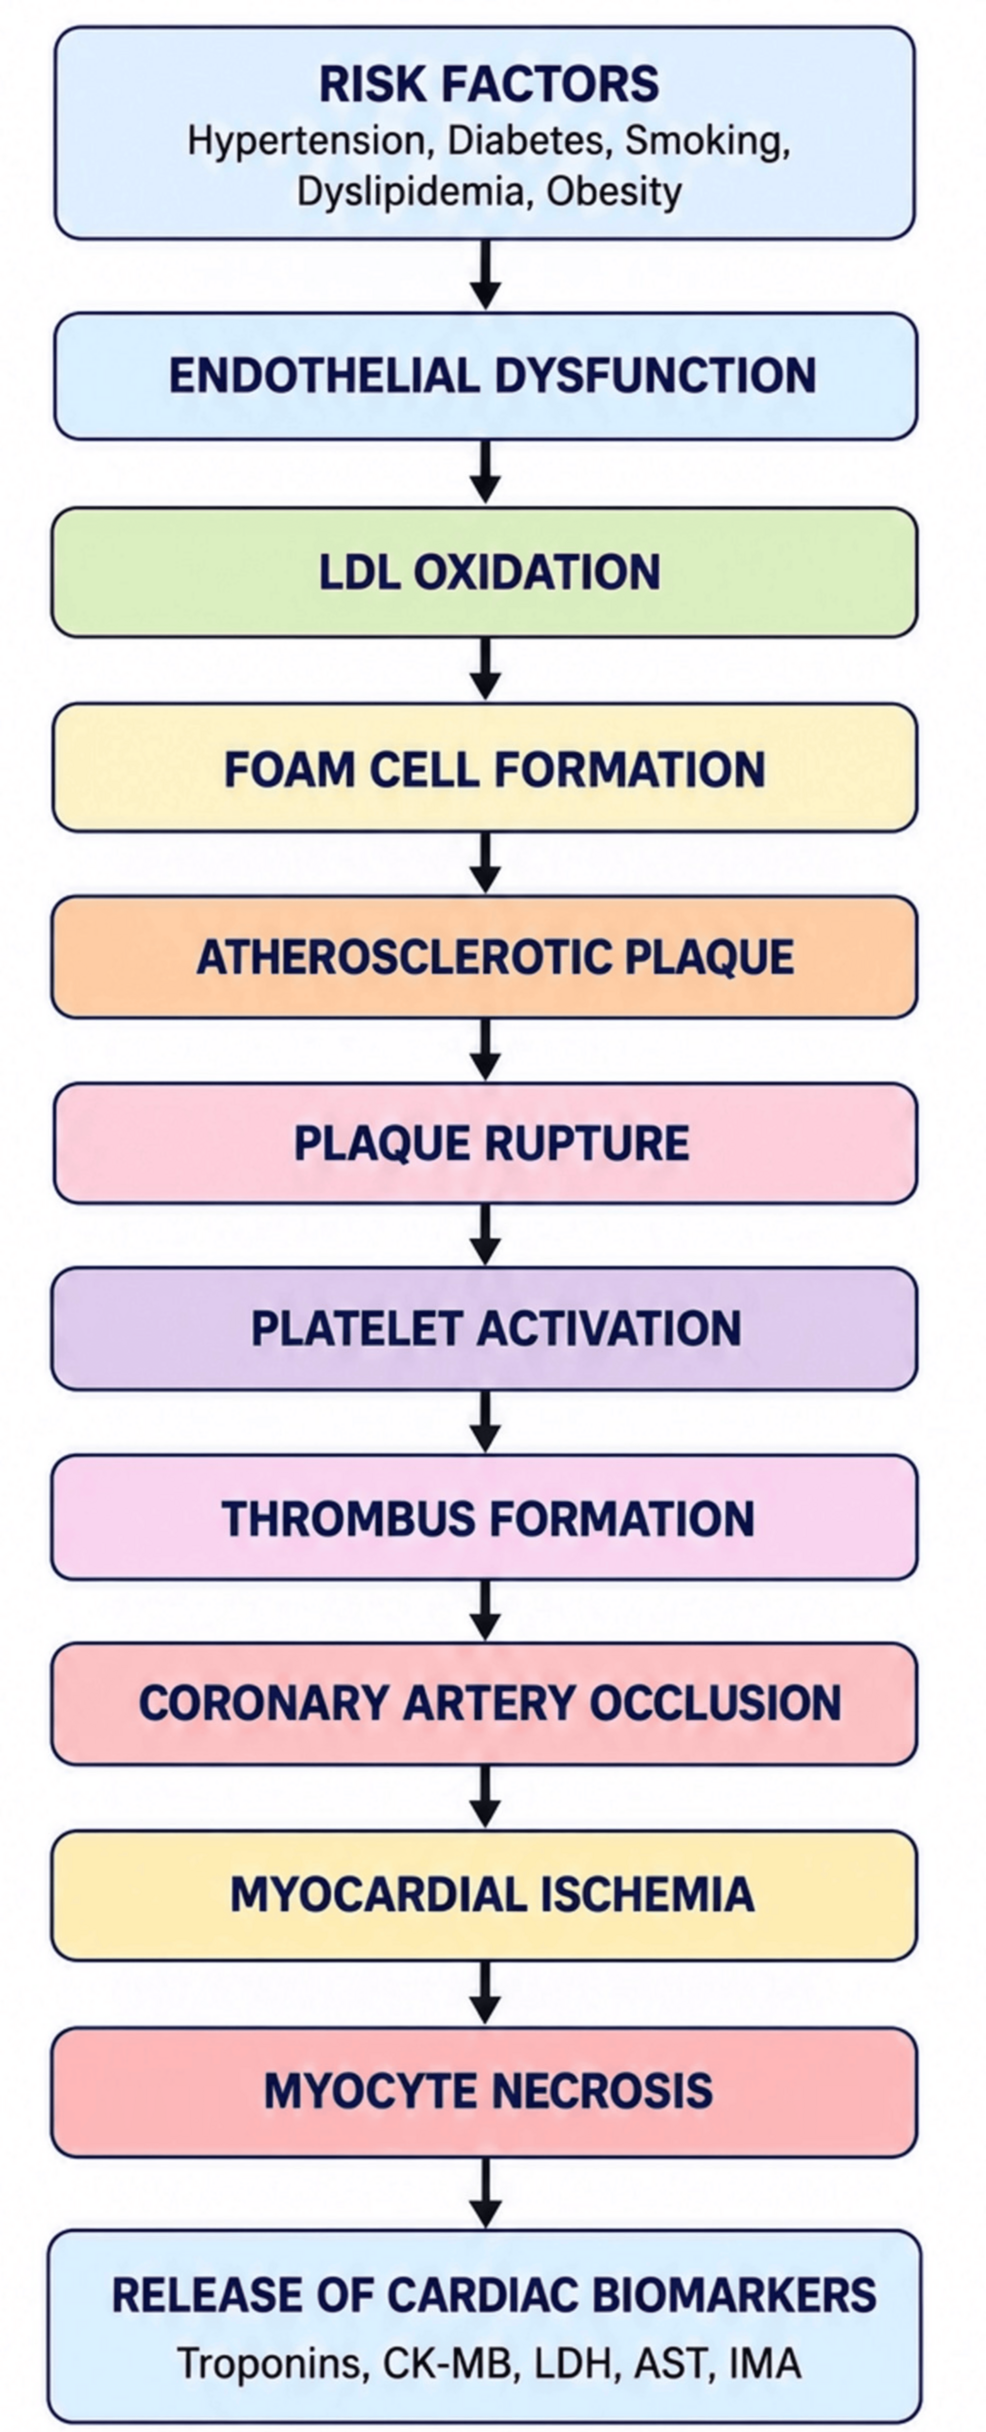
Acute myocardial infarction involves acute myocardial injury accompanied by evidence of myocardial ischemia. The condition is broadly classified into ST-elevation myocardial infarction and non-STEMI based on electrocardiographic presentation. Type 1 myocardial infarction results from acute coronary atherothrombosis following plaque rupture or erosion. Type 2 myocardial infarction stems from an imbalance between myocardial oxygen supply and demand without acute coronary atherothrombosis. More than 90% of myocardial infarctions result from coronary atherosclerosis, a chronic inflammatory disease characterized by lipid accumulation within the arterial wall. When coronary blood flow decreases, oxygen delivery falls and anaerobic glycolysis predominates. If ischemia persists for 20 to 30 minutes or longer, irreversible cardiomyocyte injury develops, characterized by loss of membrane integrity and calcium overload.
Biochemical Indicators and Ischemia-Modified Albumin Evaluation
Biochemical biomarkers provide objective evidence of myocardial damage in clinical practice. High-sensitivity cardiac troponins serve as the international reference standard for detecting myocardial injury, though a single measurement very early after symptom onset may be insufficient to exclude acute myocardial infarction. Ischemia-modified albumin represents an alternative biomarker that alters its amino-terminal region during myocardial ischemia due to oxidative stress, acidosis, and reactive oxygen species. This biochemical change reduces the ability of circulating albumin to bind transition metals such as cobalt. The albumin cobalt-binding assay measures unbound cobalt to determine ischemia-modified albumin concentrations, which typically range normally between 60 and 85 U/mL. While ischemia-modified albumin demonstrates high sensitivity during the initial hours following ischemia, its specificity remains lower than that of cardiac troponins because levels also rise in conditions such as stroke, pulmonary embolism, sepsis, chronic kidney disease, and liver disease.
Conventional Biomarkers and Clinical Interpretation
Conventional markers retain distinct diagnostic value despite the widespread adoption of high-sensitivity assays. Creatine kinase-MB constitutes approximately 15% to 20% of total creatine kinase activity in the myocardium and rises within three to six hours after symptom onset. Because creatine kinase-MB normalizes relatively rapidly after infarction, it retains an important role in detecting reinfarction when assessed alongside recurrent ischemic symptoms and electrocardiographic changes. Reference ranges for creatine kinase-MB include mass <5 ng/mL and activity <25 U/L, though elevations also occur in skeletal muscle injury, trauma, and chronic renal disease. Lactate dehydrogenase and aspartate aminotransferase continue to provide supportive diagnostic information and educational significance in clinical settings where advanced cardiac assays are unavailable.