
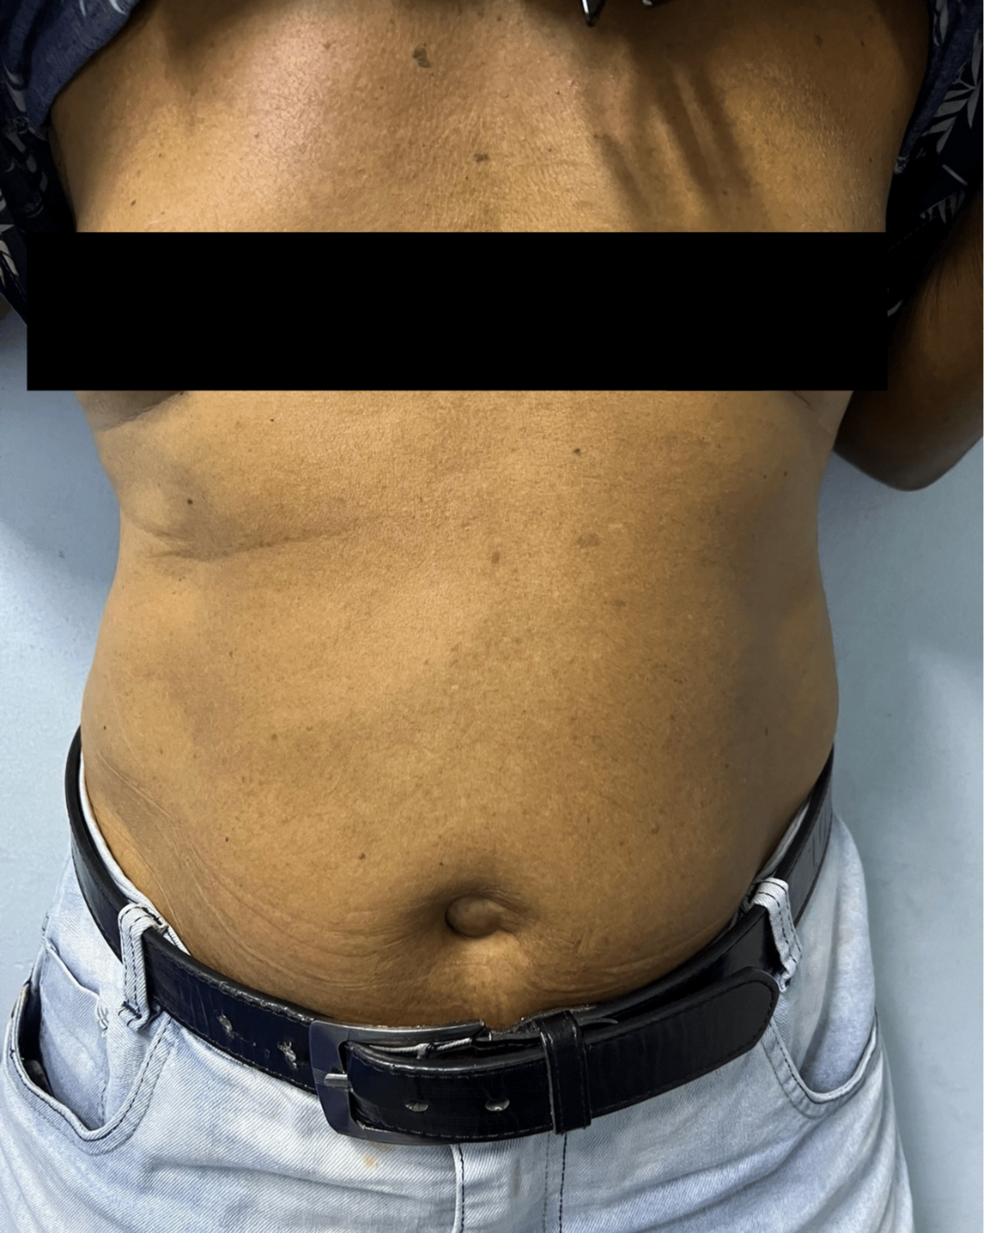
Paraumbilical vein mimics umbilical hernia in patient
- A 77-year-old male patient evaluated at the Liver Institute of Pernambuco in Brazil presented with a 2 cm umbilical protrusion that was initially considered an umbilical hernia before...
- The patient initially sought medical attention in February 2024 when routine preoperative testing for a urological procedure revealed thrombocytopenia, leading to a diagnosis of chronic hepatitis C virus...
- To investigate the umbilical mass prior to elective surgical repair, clinicians requested abdominal wall ultrasonography and a complete abdominal scan.
A 77-year-old male patient evaluated at the Liver Institute of Pernambuco in Brazil presented with a 2 cm umbilical protrusion that was initially considered an umbilical hernia before diagnostic imaging revealed a patent, recanalized paraumbilical vein associated with portal hypertension.
Clinical Presentation and Diagnosis at the Liver Institute of Pernambuco
The patient initially sought medical attention in February 2024 when routine preoperative testing for a urological procedure revealed thrombocytopenia, leading to a diagnosis of chronic hepatitis C virus infection. He subsequently received a 12-week course of sofosbuvir and velpatasvir between March 2024 and May 2024, achieving a sustained virological response with undetectable HCV-RNA by August 2024. During a routine outpatient follow-up in January 2026, clinicians identified a painless, compressible 2 cm umbilical protrusion with normal overlying skin and no detectable venous hum. Laboratory evaluations conducted in February 2026 classified the patient as Child-Pugh class A with a MELD 3.0 score of 11, reflecting preserved hepatic function despite underlying chronic liver disease.
To investigate the umbilical mass prior to elective surgical repair, clinicians requested abdominal wall ultrasonography and a complete abdominal scan. The imaging revealed hepatic volumetric redistribution, irregular liver contours, and a portal vein measuring 1.2 cm in diameter. Subsequent Doppler ultrasonography of the abdominal wall demonstrated dilation of the ascending portion of the left portal vein branch communicating directly with the ligamentum teres. This vascular mapping confirmed extensive portosystemic collateral circulation and caput medusae, with venous drainage directed into the inferior epigastric veins.
Complications and Vascular Risks of Misidentified Umbilical Masses
Recognizing the vascular etiology of an apparent umbilical hernia in patients with chronic liver disease is critical to avoiding severe clinical complications. Inadvertent surgical injury to these vessels may result in severe, potentially life-threatening hemorrhage. The differential diagnosis for periumbilical protrusions in this patient population includes umbilical hernias, vascular collateralization, or potentially both. Doppler ultrasonography serves as an imaging modality that demonstrates vascular flow and collateral extent, preventing unnecessary operations.
Following the identification of the recanalized paraumbilical vein and superficial venous collaterals, surgical intervention was contraindicated. The patient remained under clinical follow-up at the Liver Institute of Pernambuco. However, further details regarding whether the patient underwent endoscopic screening for esophageal varices, subsequent management, and long-term outcomes remain unavailable.