
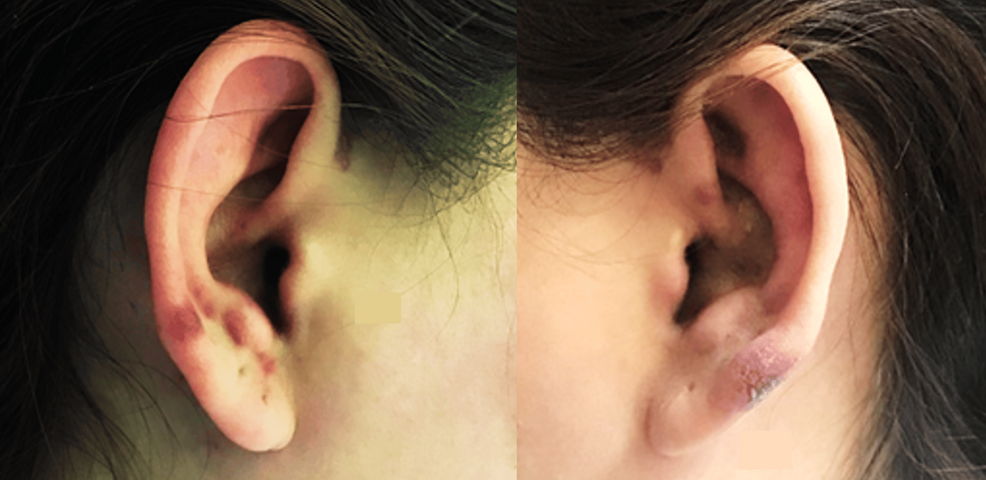
Atypical Presentation of Systemic Lupus Erythematosus Presenting as Earlobe Purpura and Severe Thrombocytopenia
- A 31-year-old woman with purple earlobes and severe fatigue was diagnosed with systemic lupus erythematosus.
- The patient arrived at the emergency department reporting a two-week history of purple discoloration on both earlobes without any prior trauma.
- Computed tomography imaging of the neck, thorax, abdomen, and pelvis demonstrated enlarged bilateral cervical, axillary, upper mediastinal, and bilateral iliac lymph nodes.
A 31-year-old woman with purple earlobes and severe fatigue was diagnosed with systemic lupus erythematosus.
Patient Discovers Unusual Earlobe Purpura
The patient arrived at the emergency department reporting a two-week history of purple discoloration on both earlobes without any prior trauma. The lesions measured between two and ten millimeters and featured mild scaling on the skin. She also reported fatigue, gum bleeding, epistaxis, and intermenstrual bleeding over the preceding week. Initial blood tests revealed a platelet count of 8 x 10⁹/L alongside normocytic anemia with a hemoglobin level of 92 g/L.
Medical Teams Investigate Conflicting Blood and Lymph Results
Computed tomography imaging of the neck, thorax, abdomen, and pelvis demonstrated enlarged bilateral cervical, axillary, upper mediastinal, and bilateral iliac lymph nodes. These findings raised concern for a lymphoproliferative malignancy. Bone marrow aspiration and trephine biopsy were performed, along with an ultrasound-guided cervical lymph node biopsy. Upon consultation, rheumatology experts noted that vasculitis was unlikely to account for the severity of the blood test abnormalities seen, particularly the drop in platelets. The differential diagnosis included SLE given the combination of cutaneous findings and hematological abnormalities.
Autoimmune Serology Confirms Systemic Lupus Erythematosus
The patient’s presenting complaint of purple earlobes is an unusual cutaneous manifestation. Because autoimmune test results provided ample proof to confirm the diagnosis, the ear lesions were not subjected to a biopsy in this instance.
Secondary Hyperinflammatory Syndrome Complicates Hospital Course
Because secondary HLH was suspected in this scenario, it created diagnostic hurdles, though the likelihood of hemophagocytic syndrome can be calculated using the HScore based on these factors: (1) underlying immunosuppression, (2) fever, (3) organomegaly, (4) ferritin, (5) triglycerides, (6) aspartate aminotransferase, (7) fibrinogen, (8) cytopenia, and (9) hemophagocytosis. The patient showed a ferritin concentration of 347 µg/L on the second day of her hospital stay, which climbed to 5,823 µg/L by Day 8. Evaluating the patient on Day 8 of her hospital stay yielded an Hscore of 172 points, pointing to a calculated likelihood for HLH of 54-70%.
Rituximab Infusion Restores Platelet Counts Before Discharge
Following a 1,000 mg intravenous dose of rituximab, the patient experienced a more than threefold increase in her platelet count over four days—rising from 19 x 10⁹/L on Day 11 of admission to 68 x 10⁹/L on Day 15—while her hemoglobin leveled out and her ferritin dropped to 993 µg/L. Sixteen days post-admission, she left the hospital with instructions for a second 1,000 mg rituximab dose scheduled two weeks after the first. Ten months following her initial hospital visit, she continues taking 1,000 mg of mycophenolate mofetil twice a day alongside 200 mg of hydroxychloroquine once daily, having successfully tapered off oral prednisolone. Recent laboratory evaluations indicate a stable hemoglobin level of 127 g/L, alongside platelet counts that have held steady above 200 x 10⁹/L over the course of several months.